
HackitRx 2026 landscape survey
The Landscape Files
63 tools examinedThese files are the single home for what already exists. Read the case for the gap in the problem statement files, and the build that answers it in the solution files.
Sixty-three haemophilia apps, symptom checkers, national triage services, telehealth platforms, clinical guidelines, informal workarounds and other-condition action plans, read against four tests, so the gap is measured rather than asserted.
The four tests
Every entry below is read against the same four questions, drawn from the clinical evidence in the WFH files and the patient interviews in the patient journey file. A tool has to pass all four to close the gap. Nothing built for haemophilia passes more than two.
- 1
Is it open at 2am?
NurseFirst runs 8am to 11pm; the haematology resource nurse is office-hours only; outside those hours a non-life-threatening 995 call reverts to standard fire and ambulance protocols. A service that closes fails this test before it answers anything.
- 2
Does it know this patient?
Factor type, severity, inhibitor status, target joints, product and dose on hand. Without those, any answer is a guess dressed as advice. Apps hold this data and give no advice; services give advice and hold no data.
- 3
Does it read the site, not the severity?
Haemophilia inverts ordinary triage. In one head-trauma series, 72.9% of episodes showed no symptoms at all, and the CHOP pathway calls for factor correction alongside imaging, not after it. A joint aura with nothing visible is the treat-now moment. A tool that grades by how bad it looks grades this condition backwards.
- 4
Does it end in an action?
A dose, a destination and a handover the receiving clinician recognises, not a log entry, a ranked differential, or "consult your doctor", which at 2am restates the problem rather than answers it.
What already exists
Seven categories. The first six are things a Singapore family could plausibly reach for tonight. The seventh is what solved this exact problem for other conditions, evidence the build is buildable, not just desirable.
Category A
Haemophilia apps
Twenty-two examined, across nine countries. Real, funded, decade-old, and built for something else. A 2021 Frontiers in Medicine review sorts every one into three functions: dose optimisation, bleed and infusion logging, adherence reminders. None of those three is a decision.
florio HAEMO
What it does
Estimates plasma factor level between doses as a single number and logs injections, bleeds, pain and wellbeing. A Sobi-funded survey of 66 users found 92% satisfied and 78% logging consistently, but the authors state plainly it does not support on-demand therapy: treating a bleed that is happening now.
Where it stops: a caregiver at 2am gets a modelled percentage, not an instruction. It exists to produce a trend for the next clinic visit, and its caregiver mode only covers children under 13.
myWAPPS and WAPPS-Hemo
What it does
The most clinically sophisticated tool here. WAPPS-Hemo builds an individualised factor VIII or IX curve from sparse blood samples; myWAPPS renders it, showing live concentration and a warning zone. It cannot be self-started: a physician must complete the pharmacokinetic report on wapps-hemo.org first. The Coalition for Hemophilia B lists this as its leading con; its verdict on the category: emergency guidance is not discussed.

Where it stops: it answers what my factor level is right now with real rigour, but has no vocabulary for a swollen knee in front of me, and fails anyone whose centre never ran the sampling.
Microhealth Bleeding Disorders
What it does
The best-reviewed tool here, started by a man with severe haemophilia A with a Columbia researcher. Tracks infusions and bleeds, scans lot numbers, monitors home stock, and notifies the treatment centre nurse when a bleed is logged.
The best Hemo app, hands down. I can send out logs to the HTC before comp visits! Easy peesy.
Abby from Minnesota, 5 stars, 14 Oct 2025, Apple App Store4.8 from 407 ratings. Across nearly a decade of feedback, nobody asks the app what to do about a bleed; they ask for more categories and better scanning. The category has trained its users not to expect a decision from it.
Where it stops: it routes information to a nurse after the event and does not evaluate a bleed while it is happening.
HemMobile
What it does
Logs each infusion's date, time, site and reason, captures lot and expiry by camera, photographs a bleed to send to the treatment centre, and sets reorder reminders. Its own App Store gallery image states: this application is not intended for curing, treating, seeking treatment for, managing, or diagnosing a specific disease, disorder, or any specific health condition. The clearest statement here that the category isn't built for the 2am question comes from the manufacturer's own marketing.
Upon entering the updated app, all of my infusion and bleed logs from the past year were totally GONE.
Tyler B16, 1 star, v6.0.0, 29 Mar 2024, Apple App Store2.9 from 7 ratings, a decade after launch, for a Pfizer-backed tool: data loss and crashes, before any question of guidance arises.
Where it stops: it disclaims the entire job in its own store copy. Photograph the bleed and send it, and nobody reads it until Monday.
Haemtrack
What it does
The UK's national electronic home therapy diary, more than 2.5 million treatment records entered since launch, compulsory for home delivery. Even at 90% centre coverage, adherence to the logging itself has never been complete.
Where it stops: it exists to feed a clinical registry, recording what treatment was given after it was given. Compliance infrastructure, nothing else.
HIRT, the Hemophilia Injury Recognition Tool
What it does
The one tool here built to help someone decide about an injury rather than record one, scoped to young men 18 to 35 with mild haemophilia facing a minor injury. A feasibility study of 12 men found perceived confidence in self-management rose significantly after use (p=0.004), self-reported rather than measured.
Where it stops: proof the shape works. It excludes severe and moderate haemophilia facing an ambiguous or serious bleed, exactly the population here, and is Canadian, unavailable here, undeveloped since the study.
Eyes on Haemo
Why this one matters more than its feature list
It surfaced only through a direct query to Apple's search index, the closest regional peer to this project anywhere. Hong Kong partnered its society with a university and a charitable trust to build it; Singapore has the society, two academic medical centres, the same problem, and has not. In its own words it is tailor-made to record, review and share bleeding and injection events.
Where it stops: no triage logic, no red flags, the same structured logging tool as the rest of the category. Its value here is as a delivery model, evidence that shape is fundable in this region.
Also examined in this category
- myPKFiT
- Takeda's FDA-cleared dosing software, tied to two factor VIII products, gated by age, weight and clinician-run sampling. Its own copy: "Only download this... if you have been provided with a QR code by your treating physician." Zero ratings on both US and UK stores a decade in.
- MyABDR, myWBDR and MyCBDR
- Australia's, the WFH's and McMaster's registry apps, feeding national and world bleeding disorder registries: record product, quantity and timing for research. Registration requires centre approval. Registry infrastructure, like Haemtrack; the latter two carry zero ratings.
- Care for Haemophilia
- An Indonesian university app filed under Education, whose store description opens in capitals: THIS APP DOES NOT PROVIDE MEDICAL CONSULTATION. The bluntest self-disclaimer in these files.
- Bleeder
- Austria, one developer, exports the diary as a PDF. Its configurable unit-ceiling warning is the closest thing to a rule-based alert here, but fires on a number the user chose, not the bleed.
- MoHaemophilia
- Mauritius: built by the national association as a digital replacement for the paper health booklet. The same category at the smallest scale found.
- ATHNadvoy, HemaGo, HemoCoach, Hemotrack and IHTC
- US logging and centre-communication apps, a discontinued factor tracker, an exercise-plan app, and a clinician-only reference tool. None has bleed-decision logic.
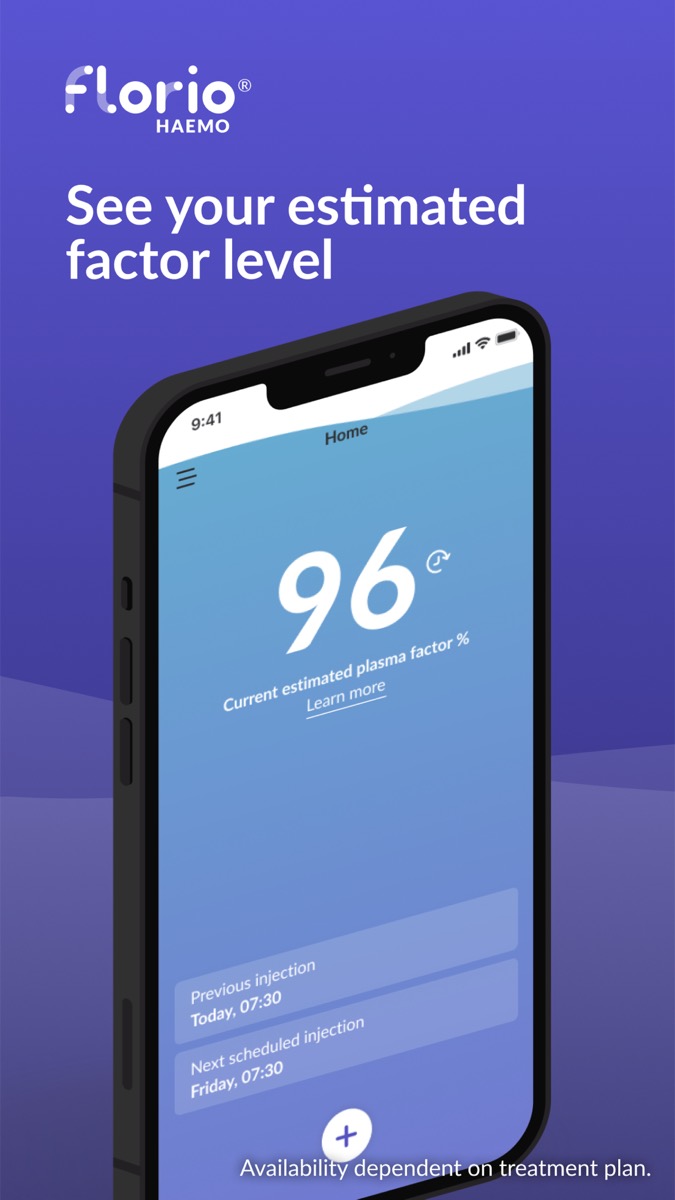
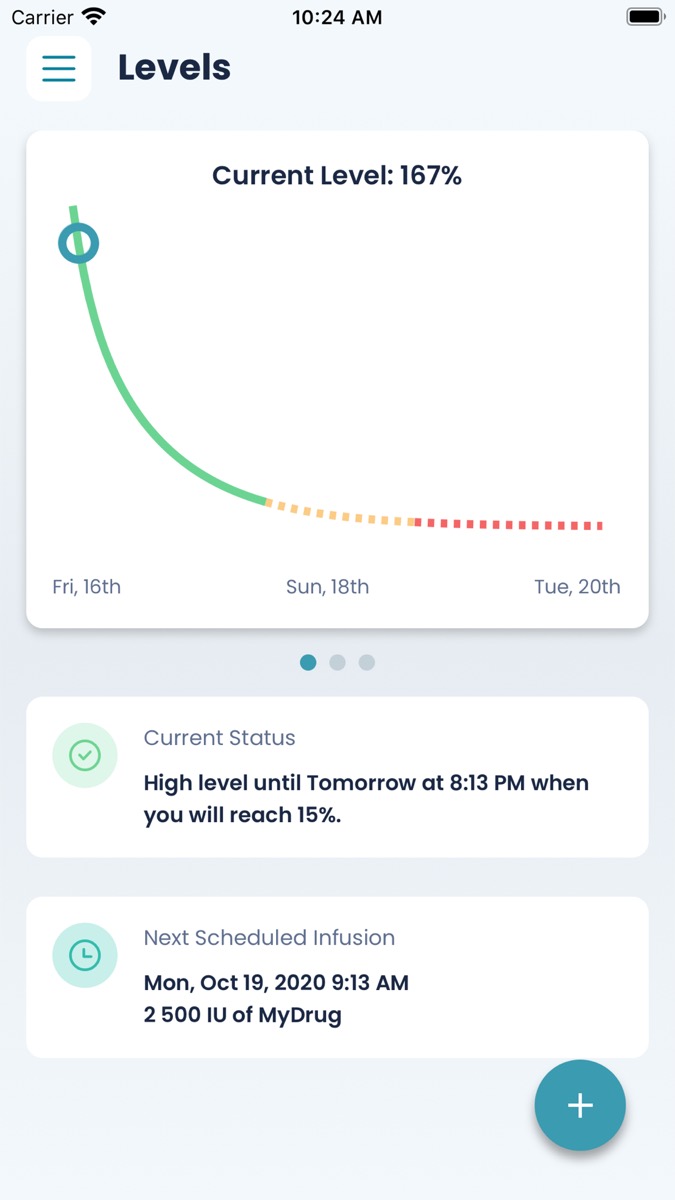
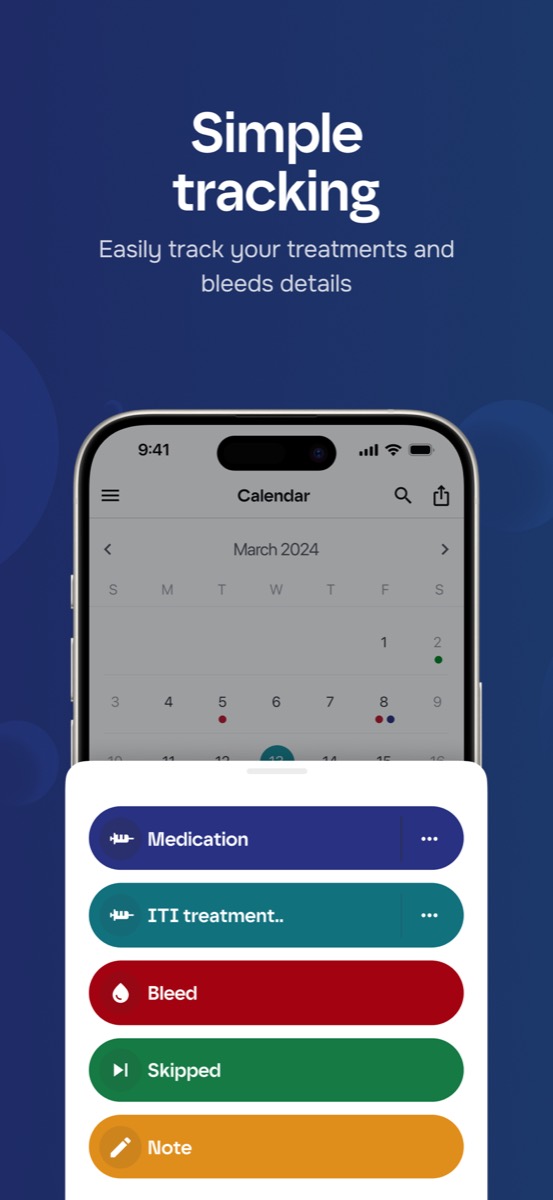
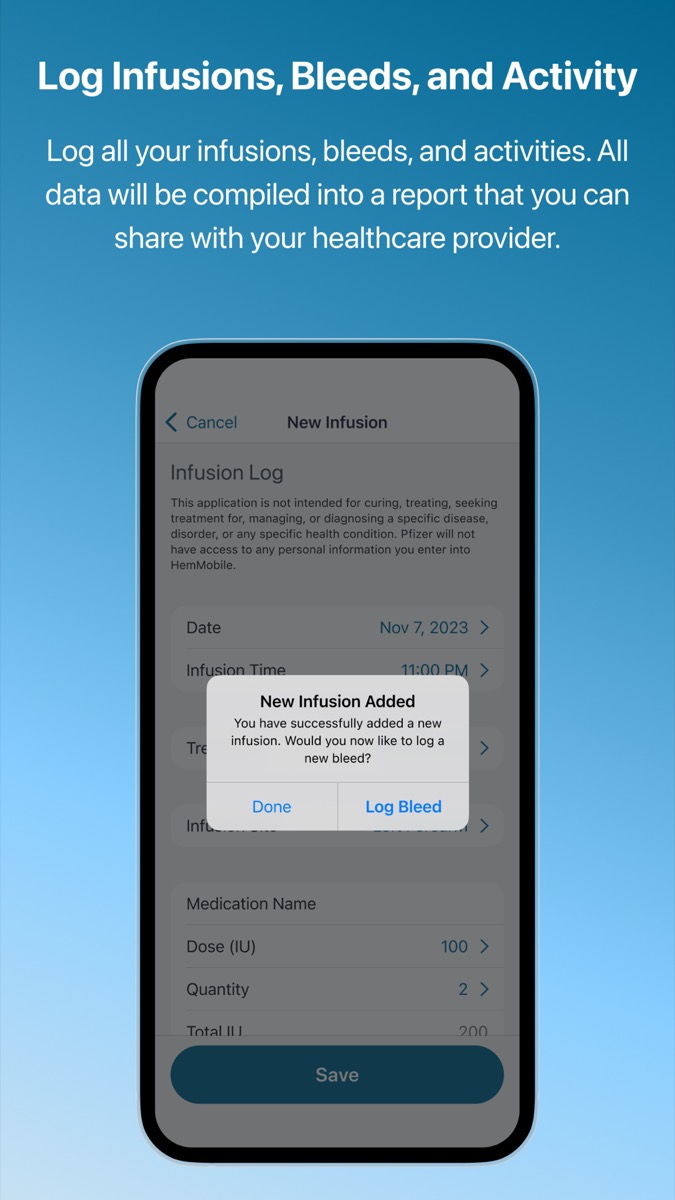

Five screens, four apps, from the developers' own App Store galleries, 3 September 2026. Every one is a number, a chart or a form. None is an instruction.
The category gap: a scoping review of 16 telehealth studies found telemonitoring showed no significant effect on outcomes like joint health, and adherence decayed from roughly 95% to 85% over a study year. A Hong Kong survey of 56 patients and parents found they want exactly what the category gives them: infusion logging (87.5%), bleed documentation (85.7%), secure delivery to the care team (71.4%). Real-time decision support does not appear in the ranked list. After fifteen years, the users have stopped asking for it.
And nothing here is Singaporean: no haemophilia app has been built by HSS, SingHealth, NUH or KKH. florio HAEMO and HemMobile 404 on the Singapore App Store; Microhealth and myWAPPS have too few local ratings to display. Hong Kong, a market of comparable size, has an app built by its society with a university and a charitable trust; Singapore has the society, the hospitals, the same 280 patients, and no equivalent.
Category B
Generic symptom checkers and AI triage
Twelve examined. The category a family actually reaches for at 2am, because it is already on their phone, and the one with the deepest published evidence, which is not reassuring.
Ada Health
What it does
A branching question sequence returning a ranked list of possible conditions with an urgency recommendation. The best performer in the largest head-to-head study of the category: Gilbert et al.'s 2020 BMJ Open comparison had Ada placing the correct condition in its top three 71% of the time, against 38% for other apps and 82% for doctors.
This app really helps reassure me that it's (almost always) all on my head. Helps provide me with peace of mind.
ChiefJake149, 28 Nov 2023, Apple App StoreThis is the category's self-description: the product these apps deliver is reassurance. For haemophilia, reassurance is the failure mode.
Where it stops: the best of them still has no way to know it is speaking to someone with a factor VIII level under 1%. Its priors are built on the general population, and a tingling ankle is not an intra-articular bleed.
Babylon Health, and what happened to it
Why it belongs in these files
Not as a competitor, since it no longer exists, but as the category's clearest documented safety record. UK oncologist David Watkins spent roughly three years from 2017 testing its chatbot, going public on BBC Newsnight in February 2020: identical chest-pain symptoms for a man and a woman produced different advice, the man sent to an emergency department with heart attack information, the woman told to see a GP in six hours with panic attack information. MHRA's clinical director told Watkins his concerns were valid; the CQC found Babylon's GP at Hand was not providing safe care in some areas, and Babylon fought the regulator in the High Court to block the report, lost, and paid costs. It filed for bankruptcy in 2023.
Where it stops: the best-funded consumer triage chatbot ever built produced gender-biased cardiac advice, fought its own regulator in court, and is gone.
WebMD Symptom Checker
What it does and how well
Free-text and checkbox symptom entry returning a list of possible conditions. The most-tested tool in the field, its primary-diagnosis accuracy in the 2022 npj Digital Medicine review ranged from 3% to 53% depending on the condition tested. It is near-useless on some condition sets and adequate on others, and the user cannot tell which case they are in.
Where it stops: a reference library with a symptom form attached, popular because it is a place to read rather than a place to decide.
ChatGPT and other large language models
What the evidence actually shows
A 2025 JMIR study reporting 100% triage accuracy for GPT-4 Turbo scored it against the Modified Early Warning Score, a materially easier task than open-ended symptom interpretation. Rare-disease symptom-checking work finds these tools are built on published literature with incomplete data on rare diseases, so accuracy suffers. No source reports language-model performance on inherited bleeding disorders.
Where it stops: a general model answers a haemophilia question at 2am, fluently and instantly, which is the risk. It does not know this patient's factor level, has no signed clinical source, and leaves no record for the treatment centre.
Also examined in this category
- Buoy Health, K Health and Symptomate
- Three more checkers from the 2020 BMJ Open comparison: Buoy scored around 80% on safety; K Health, now routing to a paid consult, 36.0% top-three accuracy against 82.1% for doctors; Symptomate the lowest top-three accuracy (19%) but among the highest safety (97.8%). Safe and right are different achievements.
- Isabel and Mediktor
- A differential-diagnosis tool built for clinicians and offered to patients, and a Barcelona-built assessment chatbot white-labelled into health systems, 80.5% condition coverage in a 2019 ENT vignette set. Neither validated for rare disease.
- NHS 111 online, Healthdirect and Mayo Clinic
- The UK's official online triage service, which a study found did not clearly reduce demand on the phone service; Australia's government-funded tool with clinical governance mapped to real scopes of practice; and the web tool in the original 2015 Harvard benchmark. Reference tools, not decision tools.
The evidence on the category as a whole
2015 to 2022
Semigran et al. audited 23 free symptom checkers against 45 standardised vignettes: correct diagnosis first 34% of the time, triage advice correct in 49%. The same vignettes re-run five years later found median triage accuracy flat, 59.1% to 55.8%, and the task that matters here, identifying when emergency care is required, correct only 51.9% of the time. A 2022 review of 48 checkers found primary diagnosis accuracy 19% to 37.9%, triage accuracy 48.8% to 90.1%, and ophthalmic emergencies triaged correctly only 39% of the time against 88% for non-urgent cases in the same tool: reliance on symptom checkers could pose significant safety hazards.
The pattern: the category is measurably weakest at exactly the judgement a bleeding disorder needs it to be strongest at, and it has not improved. Where a tool is safe, it is safe by escalating, which recreates the over-referral this project is trying to reduce.
Why the logic inverts for haemophilia
Stated plainly
No paper found describes bleeding disorders as a case where symptom-checker logic runs backwards; this framing is the team's own, assembled from the evidence and clinical guidance above.
One. These engines are tuned on population base rates, and haemophilia affects about 10.31 per 100,000 males in Singapore: asked about a warm, sore joint, a model weights strain and minor injury above an internal bleed, because for almost everyone asking, it is.
Two. Absence of symptoms is not reassurance here. In one head-trauma series 72.9% of episodes showed no symptoms, and the CHOP pathway starts factor correction alongside imaging. A checker reading "knocked head, feels fine" returns self-care: right for the general population, wrong here.
Three. MASAC Document 257 states pain and swelling in a joint or muscle directly warrant replacement therapy regardless of investigation results, the inverse of a checker's ask more, narrow the differential, then recommend structure. The signal that matters most, the aura, a tingling warmth before any swelling, has no place in a generic question set, and is the exact input that pushes a general-purpose tool towards reassurance.
What follows: a haemophilia tool cannot be a thinned-down general symptom checker. It has to be a pre-committed decision tree carrying this condition's own inverted risk logic, which is what the precedents in Category G were built to do.
Category C
Singapore's triage and diversion layers
Eight examined. Singapore has already built a round-the-clock AI triage chatbot for parents. It is good, it is free, and it excludes this patient.
KKH U-PAL, the Urgent Paediatric Advice Line
What it does
The closest thing in Singapore to what this project proposes: a chat service performing basic medical triaging for common acute concerns and escalating to the care team when it cannot answer, to reduce unnecessary emergency visits among Priority 3 cases. Rebuilt with generative AI, it now operates around the clock at no cost.
Who it is not for
Quoted in part: "For certain pre-existing or chronic medical conditions, KKH U-PAL may not provide the specialised care your child requires... please consult directly with your child's attending doctor or designated care team." The list runs from bowel and liver disease to cancer. A bleeding disorder is not named, but is plainly a chronic, specialist-managed, haematology-led condition, the description the clause is written to capture, and the door it points to instead is closed at 2am.
Where it stops: the strongest evidence this is buildable, and generic paediatrics that stops at specialist-managed chronic disease, covers nobody over 18, and has no bleeding-disorder logic.
NurseFirst, 6262 6262
What it does
Emergency-trained nurses working from protocolised questions with physician oversight, directing callers to GPs, urgent care centres or teleconsults. In the Ministry's own words: "Outside of these hours, if a 995 call is assessed to be non-life-threatening, SCDF will deal with it according to its current protocols." Since April 2019 SCDF does not convey assessed non-emergency cases to hospital.
Where it stops: the right model, on the wrong clock. It will either over-refer or miss an inverted presentation, and between 11pm and 8am it does neither, because it is closed.
HealthHub
What it actually contains, checked rather than assumed
Biometric login, a dashboard, appointment booking, caregiver access to a dependent's records, bill payment, prescription refills, and the National Electronic Health Record. No symptom checker, triage tool or care-navigation feature anywhere.
Locked out of accessing her medications. No access granted.
sharpclaws, 4 Feb 2024, Apple App Store, on a dependent's caregiver accessWhere it stops: the national platform holds the record and books the appointment. It has never been asked to answer a question, and none of its 28,600 reviewers mentions after-hours guidance.
sgcovidcheck.gov.sg, the precedent that was switched off
What it was
Singapore's government took age, travel and exposure history and symptoms and returned an immediate care recommendation: monitor at home, or seek care in a named setting. The closest thing the state has built to a public "should I seek care and where" tool.
Where it stops: it has been retired; sgcovidcheck.gov.sg no longer resolves. Singapore builds this kind of tool when a condition is urgent enough, and decommissions it when the emergency passes; haemophilia's does not.
Also examined in this category
- GPFirst and Alexandra Hospital Urgent Care Centre
- A GP-referral discount that cut self-referred walk-ins by 36 to 40% at Changi General from 2014 to 2019, and a 24-hour walk-in centre now receiving eligible non-life-threatening ambulance cases. Evidence a middle tier exists, and that a nudge to use it works.
- 995 and SCDF, and Healthy 365
- A flat S$274 charge for a conveyed case assessed non-emergency prices the guess upward. Healthy 365, the Health Promotion Board's app, was checked and ruled out: no symptom checker, no triage.
The category gap: Singapore is building this layer deliberately: assessed nurse triage, destinations between home and the emergency department, a priced nudge, and now a generative-AI chatbot for parents around the clock. Every piece exists; none is pointed at a rare condition whose heuristics invert, and the round-the-clock piece excludes chronic specialist-managed disease by design.
Category D
Commercial telehealth
Five examined, four in full. All are available at 2am, or say they are, staffed by generalists with no access to a factor level, inhibitor status or bleed history, and most exclude emergencies in their own terms.
Doctor Anywhere
What its own terms say
Its Terms and Conditions state, in capitals: do not use the video consultation functionality on the application for a medical emergency, listing severe pain, breathlessness and anything needing physical examination as inappropriate for video. No bleeding-disorder pathway exists.
Waited over an hour for packing and delivery with no way to track location. I was in a lot of pain and in a rush, still awake at 4am waiting.
'Help((((((((', 2 stars, 14 Jan 2025, Apple App StoreWhere it stops: a generalist on a ten-minute video call, with no factor level, inhibitor status or bleed history, facing a condition where the safe-looking answer can be wrong. The defensible move is to send the family to the emergency department, the over-referral this project exists to reduce.
WhiteCoat
The honest counter-example
A WhiteCoat doctor identified a possible corneal ulcer in the reviewer's son and recommended immediate A&E since no ophthalmology clinic was open on the weekend; the son was later diagnosed with an aggressive viral infection, and the reviewer credits the early referral with preventing vision loss.
dopa23mine, 18 Oct 2021, Apple App StoreWhere it stops: the escalation worked because the doctor could see the eye. Haemophilia's dangerous bleeds cannot be seen: intracranial, retroperitoneal, iliopsoas, a compartment filling in a forearm. Recognition is the whole task, and a video call cannot do it.
MaNaDr, and the regulatory record
What the Ministry of Health found
On 16 August 2024 the Ministry directed MaNaDr to stop teleconsultation, finding more than 100,000 calls of one minute or less, the shortest one second, and over 1,500 patients issued medical certificates five or more times in one sampled month. On 24 October it moved to revoke the licence, citing an entrenched culture of disregard for clinical and ethical standards. This establishes that Singapore's generalist telehealth sector has a documented quality-control problem in exactly the format a rare-disease patient would meet at 2am, the brief generic consultation.
Where it stops: the app is still rated 4.8 by its users. Consumer satisfaction and clinical adequacy measure different things, and for a bleeding disorder only one matters.
Speedoc
What it says it is for
The one provider here that names chronic-condition follow-up as in scope, alongside mild symptoms, urgent care and specialist referrals. Anything life-threatening is routed to 995 or the emergency department.
Family needed ambulance, by the time i checked in on them they still could tell me they reached out to their many private partners and none of them responded. Better off calling 995 of 1777. Complete and utter waste of precious time when it comes to emergencies.
Lorlorxue, 1 star, 27 Mar 2022, Apple App Store, titled "Horrifying service. Avoid during emergency"A Singapore family in a real emergency told by the product that they should have called 995. A 2022 review, as recent as Apple's feed reaches.
Where it stops: the policy is correct on paper and this is what it looked like on one night. Speedoc's own answer for an emergency is the ambulance number the family was trying to avoid needing.
Also examined in this category
- Homage
- Scheduled home care and visits, 4.7 from 864 App Store ratings, the lowest Play score of the six. Built for planned care, not urgent response; reviews describe last-minute cancellations. Out of scope for an acute bleed by design.
The category gap: five products, all reachable at 2am, all good at what they are for, and none has a bleeding-disorder pathway, a way to read a factor level, or any claim to handle rare complex conditions beyond routine follow-up. Three of the five route emergencies straight back to 995 in their own terms.
Category E
Static clinical guidance
Five examined. The doctrine that answers the question is already written, published, free and correct. It is also a document, and its failure is documented in emergency department audit data.
The doctrine, and the evidence that it does not survive contact with 2am
What exists
The WFH's third-edition guidelines set the system-level expectation of round-the-clock access to emergency medicines and clotting factor. MASAC Document 257 codifies the rules: treat before diagnostic studies, treat on suspicion, assume a factor level of zero when unknown, get factor into the patient within an hour. SingHealth's own page tells families to attend the Children's Emergency at KKH Basement 1 after hours; its summary line is three words: if in doubt, treat. The field has already tried an emergency card fix: the WFH's international identity card, the UK's bleeding disorder card, and the US programme FactorFirst, built to shortcut the diagnostic workup entirely.
What happens anyway
A 2025 audit in Pediatric Blood and Cancer measured the gap between doctrine and delivery: a median 2.9 hours from triage to ordering haemostatic therapy, 4.2 hours to administration, against MASAC's one-hour standard, and fewer than a third of emergency visits ending in haemostatic therapy at all.
Where it stops: the most important finding in these files. Haemophilia already has the right doctrine and a physical delivery mechanism for it, and still fails at the point of care. The unmet need is getting a specific family to the right decision at 2am with something the receiving clinician recognises fast enough to act on.
Category F
The informal layer
Four examined, and this is the honest answer to what actually gets used. Everything above is what exists. This is what happens.
What families reach for at 2am
Spreadsheets, group chats, paper notes, memory
Spreadsheets work for routine prophylaxis and break on travel or a missed dose. Group chats are disorganised and unvalidated; patients say they disregard them. Paper discharge notes and saved screenshots are undated and specific to whichever visit produced them. When those run out, families repeat the usual dose and monitor on self-invented windows, an hour for a hip bleed, a day elsewhere, before deciding anything more.
Where it stops: this is the real incumbent, the thing any new tool has to be better than on the first night. None of it is signed, current or personal, and none leaves a record anyone can hand to a doctor.
Category G
What does give an action, for other conditions
Seven examined. Not competitors: proof the format exists, works and is evidenced, and that the only reason haemophilia lacks one is nobody has built it.
The ASCIA anaphylaxis action plan
Given to every patient prescribed an adrenaline autoinjector, in a general version plus four device-specific ones. The structure matters: recognise a defined symptom set, use the device now, call emergency services. No differential diagnosis step anywhere in it.
The lesson: at the moment of crisis, a pre-agreed instruction beats an assessment. This is the benchmark row in the scorecard below, and the only artefact here that passes all four tests.
Asthma and seizure action plans
Asthma's written, individualised traffic-light plan, green for baseline control, yellow for a defined step-up, red for urgent action, is backed by a Cochrane review of 18 trials showing it significantly reduces hospitalisations, emergency visits and nocturnal symptoms. The yellow zone is specified to the dose: a four to five-fold increase in inhaled corticosteroid for 7 to 14 days works; simply doubling it does not. Seizure action plans similarly capture type and history with step-by-step instructions, paired with a rescue benzodiazepine, and an expert panel published formal recommendations to standardise the format, the same exercise these files perform for haemophilia.
The lesson, and the warning: specificity is the active ingredient, and a good artefact does not implement itself. The same literature describes written asthma action plans as a niche practice despite the evidence behind them.
Also examined in this category
- The 15-15 rule and CGM alerting
- Fifteen grams of fast-acting carbohydrate, wait fifteen minutes, recheck, repeat, now under review since it predates continuous glucose monitors, whose predictive alerts fire when a value at or below 55 mg/dL is forecast within 20 minutes. Build something revisable, and tiered.
- Warfarin self-management
- Self-testing alone improves time in therapeutic range; self-management, self-testing plus a pre-agreed dose rule, is what reduces thromboembolic events. Uptake is still under one in seven eligible patients.
- Sickle cell disease
- A negative precedent: no widely adopted crisis action plan was found. Even in this well-known haematological emergency, the field invested in longitudinal self-monitoring, not a crisis-moment artefact.
The category gap: every one of these was built for a condition where a layperson must act correctly under stress with no clinician present, replacing open-ended assessment with a small number of pre-agreed paths. Haemophilia has the doctrine and the emergency card, and has never had the third: a personalised, always-open artefact that turns doctrine into tonight's instruction.
The scorecard
Twenty-five tools that offer an answer, read against the four tests. Places that provide care, the emergency department, urgent care centres and GPFirst, are left out as destinations, not competitors. The last row is a different condition, to show what passing looks like.
| Tool | Open at 2am | Knows this patient | Reads site, not severity | Ends in an action |
|---|---|---|---|---|
| A. Haemophilia apps | ||||
| florio HAEMO | yes | part | no | no |
| myWAPPS clinician-gated | yes | part | no | no |
| Microhealth Bleeding Disorders | yes | part | no | no |
| HemMobile | yes | part | no | no |
| Haemtrack UK only | yes | part | no | no |
| MyABDR Australia only | yes | part | no | no |
| Eyes on Haemo Hong Kong | yes | part | no | no |
| myPKFiT two products, QR-gated | yes | part | no | no |
| HIRT mild disease, minor injury | yes | no | part | part |
| B. Symptom checkers and AI triage | ||||
| Ada Health | yes | no | no | part |
| WebMD Symptom Checker | yes | no | no | no |
| Symptomate and Infermedica | yes | no | no | part |
| NHS 111 online UK only | yes | no | no | part |
| ChatGPT and other language models | yes | no | no | part |
| C. Singapore's triage layers | ||||
| KKH U-PAL under 18, excludes chronic specialist care | yes | no | no | part |
| NurseFirst 6262 6262 8am to 11pm | no | no | no | part |
| HealthHub | yes | part | no | no |
| D. Commercial telehealth | ||||
| Doctor Anywhere | yes | no | no | part |
| WhiteCoat | yes | no | no | part |
| Speedoc video 7am to midnight | part | no | no | part |
| MaNaDr | yes | no | no | part |
| E and F. Guidance and the informal layer | ||||
| WFH guidelines, 3rd edition | yes | no | yes | part |
| MASAC Document 257 written for clinicians | yes | no | yes | part |
| Bleeding disorder emergency card | yes | yes | no | part |
| Spreadsheets, chats, paper, memory | yes | part | no | no |
| ASCIA anaphylaxis action plan a different condition, for comparison | yes | yes | yes | yes |
Reading down the columns: almost everything is open at 2am, because almost everything is an app. Almost nothing knows the patient: tools that hold data give no advice, services that give advice hold no data. Only the written guidelines read by site rather than severity, and they are documents. Nothing built for haemophilia ends in an action.
The verdict
Sixty-three tools, and the field splits cleanly in two. The apps hold the patient and say nothing: they know the factor product, dose and fridge stock, and their purpose is a trend for the next clinic visit. The services speak and know nothing: a nurse line, a teleconsult doctor or a symptom checker gives an answer at 2am without the one patient record that would make it safe.
Four specific things have to be true at once, and no publicly documented tool does all four:
- It is awake between 11pm and 8am, which is when Singapore's assessed triage layer is not.
- It already knows the factor type, severity, inhibitor status, target joints and home stock: the answer is about this patient, not haemophilia in general.
- It routes on the site of the bleed rather than how bad it looks, because in this condition a head knock with no symptoms outranks a visibly swollen ankle.
- It ends in a dose, a destination and a handover the emergency department recognises, so following the advice buys the family something at the receiving end, the way GPFirst does.
The doctrine was written years ago and is free to read. The format that delivers it at 2am was solved for anaphylaxis, asthma, epilepsy and hypoglycaemia. KKH has proved Singapore will run a round-the-clock advice chatbot for parents, and excludes chronic specialist-managed conditions from it. Every component exists; nobody has assembled them for a bleeding disorder. That is the space the solution files builds into.
What these files could not verify
- Google Play figures are given for the six Singapore consumer apps, read from live listings, and omitted for the haemophilia apps, where the Play page could not be read reliably: one attempt returned a review count belonging to an unrelated app.
- florio HAEMO and myWAPPS each carry a single App Store rating; myPKFiT, myWBDR, MyCBDR, Eyes on Haemo, Care for Haemophilia, Bleeder and MoHaemophilia carry none, and no review text exists to quote for any of them.
- The Speedoc reviews quoted are from 2022, as far back as Apple's feed reaches, not current sentiment; no outcome data for the nationwide NurseFirst trial could be found up to September 2026.
- Whether a bleeding disorder falls inside KKH U-PAL's exclusion list is a genuine ambiguity in KKH's own wording, read here as unresolved; the inversion argument in Category B is the team's own synthesis, and no source states symptom-checker logic runs backwards for haemophilia.
- Two directly relevant papers, the 2025 npj Digital Medicine comparison of checkers, language models and laypeople, and the 2020 Medical Journal of Australia evaluation, were paywalled, so neither is cited with figures.
Sources
- Zapotocka et al., florio HAEMO: A Longitudinal Survey of Patient Preference, Adherence and Wearable Functionality, Advances in Therapy, 2024
- florio HAEMO, Apple App Store listing and florio.com, checked 3 Sep 2026
- WAPPS-Hemo, McMaster University Health Information Research Unit
- myWAPPS, Apple App Store listing, v4.3, checked 3 Sep 2026
- Microhealth Bleeding Disorders, Apple App Store, 4.8 from 407 ratings, checked 3 Sep 2026
- Coalition for Hemophilia B, What hemophilia tracking app should I be using
- HemMobile, Apple App Store listing and gallery, v6.0.1, checked 3 Sep 2026
- Hay et al., The haemtrack home therapy reporting system: design, implementation, strengths and weaknesses, Haemophilia, 2017
- UKHCDO National Haemophilia Database; University Hospital Southampton Haemtrack patient factsheet
- National Blood Authority Australia, MyABDR; Haemophilia Foundation Australia
- Takeda, myPKFiT for ADYNOVATE launch release, 2020
- Canadian Hemophilia Society, HIRT; Are you HIRT? feasibility study, n=12
- Dirzu et al., Mobile Health Technology for the Personalized Therapy of Hemophilia, Frontiers in Medicine, 2021
- Qian et al., Telehealth Interventions for Improving Self-Management in Patients With Hemophilia: Scoping Review, JMIR, 2019
- Technology Acceptance Among Patients With Hemophilia in Hong Kong, JMIR Formative Research, 2021, n=56
- Semigran et al., Evaluation of symptom checkers for self diagnosis and triage, BMJ, 2015
- Triage Accuracy of Symptom Checker Apps: 5-Year Follow-up Evaluation, JMIR, 2022
- Wallace et al., The diagnostic and triage accuracy of digital and online symptom checker tools, npj Digital Medicine, 2022
- Gilbert et al., How accurate are digital symptom assessment apps, BMJ Open, 2020
- TechCrunch, First do no harm, Feb 2020, and MHRA comment reported Mar 2021
- The Register, Babylon withdraws challenge against health regulator report, Dec 2017
- TechCrunch, The fall of Babylon, Aug 2023
- Ada Health, Apple App Store listing and reviews, checked 3 Sep 2026
- WebMD Symptom Checker, Apple App Store listing and reviews, checked 3 Sep 2026
- Evaluation of Artificial Intelligence for Patient Self-Triage, 2025, NHS 111 online against ChatGPT and Gemini
- Patient Triage and Guidance in Emergency Departments Using Large Language Models, JMIR, 2025
- Fabry disease mixed-methods study on rare-disease symptom checkers; FindZebra scope statement
- Children's Hospital of Philadelphia, Hemophilia with Head Trauma Clinical Pathway
- Head trauma in haemophilia, 72.9% asymptomatic presentation, PubMed 29873151
- National Bleeding Disorders Foundation, MASAC Document 257, approved 2 Dec 2019
- KK Women's and Children's Hospital, U-PAL; Synapxe, KKH U-PAL chatbot, checked 3 Sep 2026
- MOH, Nation-wide trial to refer non-life-threatening 995 calls to the NurseFirst helpline, 30 May 2025
- MOH, GPFirst; Changi General Hospital, GPFirst: a journey of changing attitudes and improving patient care
- NUHS, Alexandra Hospital to receive eligible non-life-threatening cases, 2025
- HealthHub SG, Apple App Store, 4.7 from about 28,600 ratings; Synapxe HealthHub programme page
- Health Promotion Board, Healthy 365, feature set checked 3 Sep 2026
- MOH Office for Healthcare Transformation, COVID-19 Symptom Checker Launched, 2020; sgcovidcheck.gov.sg no longer resolves, checked 3 Sep 2026
- SCDF, Emergency Medical Services
- Doctor Anywhere, Apple App Store listing and Terms and Conditions, checked 3 Sep 2026
- WhiteCoat, Apple App Store listing and reviews, checked 3 Sep 2026
- Speedoc, Apple App Store listing and published FAQ
- MOH, MaNaDr Clinic Instructed to Stop Provision of Outpatient Medical Services via Teleconsultation, 16 Aug 2024
- MOH, Regulatory Action Against MaNaDr Clinic and Doctors Involved in Potential Professional Misconduct, 24 Oct 2024
- Homage, Apple App Store listing, checked 3 Sep 2026
- Srivastava et al., WFH Guidelines for the Management of Hemophilia, 3rd edition, Haemophilia, 2020
- SingHealth, Haemophilia (Childhood Illnesses)
- World Federation of Hemophilia International Identity Card; UKHCDO Bleeding Disorder Card; NBDF FactorFirst
- Improving Time to Bleeding Disorder Treatment in the Emergency Department, Pediatric Blood and Cancer, 2025
- ASCIA, Action Plans for Anaphylaxis, 2023 revision
- Cochrane review of written asthma action plans, 18 randomised trials; npj Primary Care Respiratory Medicine, Solving the mystery of the yellow zone
- American Academy of Pediatrics, Seizure Rescue Medications and Seizure Action Plan; Recommendations for development of acute seizure action plans
- The 15-15 rule systematic review; Real-World Evidence and Glycemic Improvement Using Dexcom G6 Features
- Warfarin patient self-testing and self-management outcomes literature
- Haemophilia Society of Singapore, Treatment in Singapore
- Team primary research, Patient Journey and Pain Points, HSS Summary, 30 Aug 2026
- myPKFiT for Patients, Apple App Store id 1208272930, Takeda, checked 3 Sep 2026
- Eyes on Haemo, Hong Kong Haemophilia Society with The Chinese University of Hong Kong, funded by the Hong Kong Jockey Club Charities Trust, Apple App Store id 1589167372
- myWBDR, World Federation of Hemophilia, Apple App Store id 1544989257; MyCBDR, McMaster University, id 1080642378
- Care for Haemophilia, Universitas Lambung Mangkurat, Apple App Store id 1672502386
- Bleeder, Hannes Jung, Apple App Store id 1137943402; MoHaemophilia, Haemophilia Association of Mauritius, id 6499239638
- Google Play listings for HealthHub, Doctor Anywhere, WhiteCoat, Speedoc, MaNaDr and Homage, captured 3 Sep 2026
A HackitRx 2026 entry by Team Bleedwise: Ariel Tan, Rachel Koh, Myo Myo Swe Oo and Gerald Ho. See the team.
App-store ratings, reviews and screenshots were captured 3 September 2026 and change continuously. Full source library at the WFH files. Companion to the case files, the patient journey file and the solution files.